
Medical Providers
As medical professionals, we expect you have many questions about a new technology. We created this page with you in mind to help answer your questions with reasonably technical responses. We are happy to share the published sources for the information provided here. You can also search our Bone Health Journal for other posts and information.
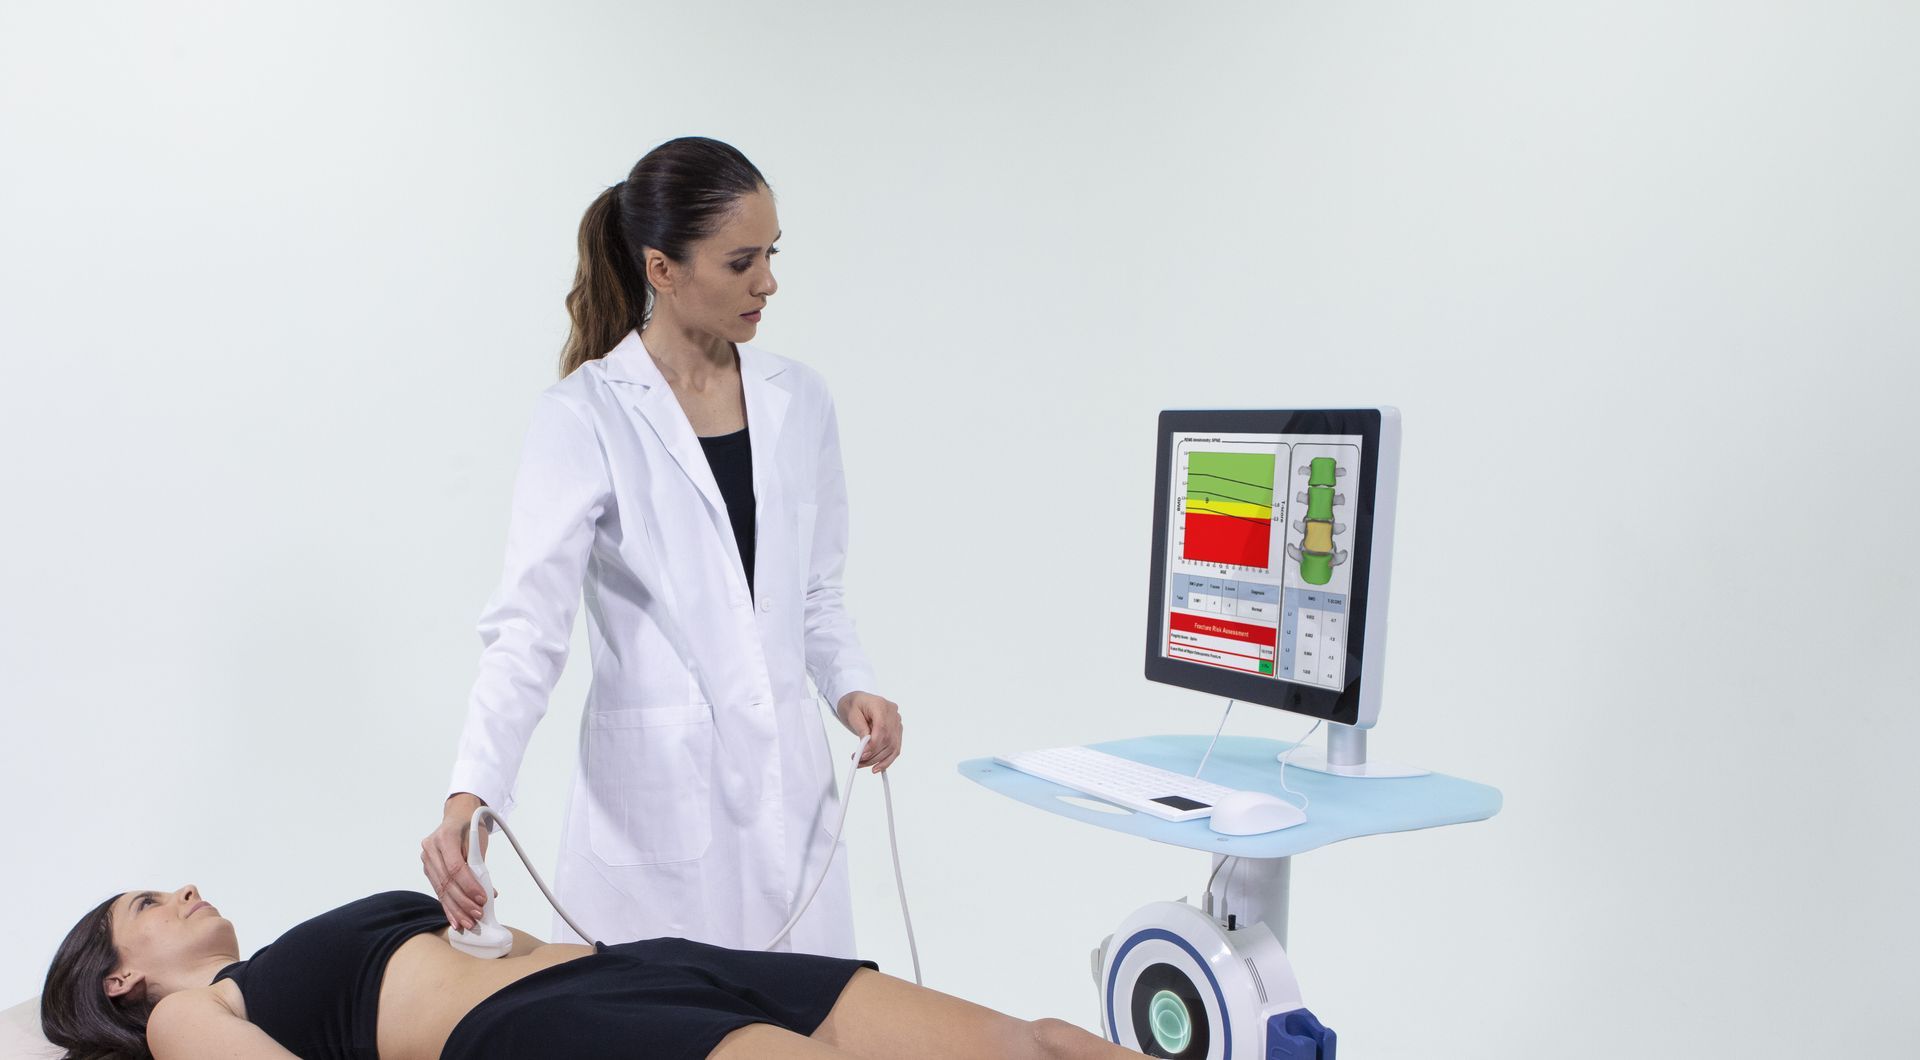
Bring REMS to Your Medical Practice
Want to offer REMS scanning at your practice or host a REMS event at your location? We are looking for providers who desire access to this important diagnostic tool. We have information to share about the options for partnering with other providers in your area to share equipment or bring the equipment to your practice.
FAQs
What are Echolight and REMS?
Radiofrequency Echographic Multi Spectrometry (REMS) is a quantitative ultrasound technology that assesses and reports clinically significant characteristics of human bone in a manner that complies with the World Health Organization (WHO) established criteria for the diagnosis of osteoporosis. The predecessor of the REMS technology was Quantitative Ultrasound (QUS). Although QUS was found to be a capable method of predicting fracture risk, QUS has technical limitations in reliability determining Bone Mineral Density (BMD). Therefore, QUS cannot not be used as a clinically valid method to diagnose and treat osteoporosis based on the WHO guidelines.
What is Radiofrequency Echographic Multi Spectrometry (REMS) and how is it done?
REMS is a novel technology that targets specific bones with pulsed ultrasound waves and receives the backscatter radiofrequency (RF) signals from the insonified bone. The backscatter RF signals are then filtered and analyzed. It has been established that the raw backscatter RF signals contain relevant information after interacting with the targeted bone microarchitecture. Therefore, the underlying principle of the REMS analysis is that the backscatter RF signals that have interacted with the bone contain information on both density and quality.
How are REMS results reported?
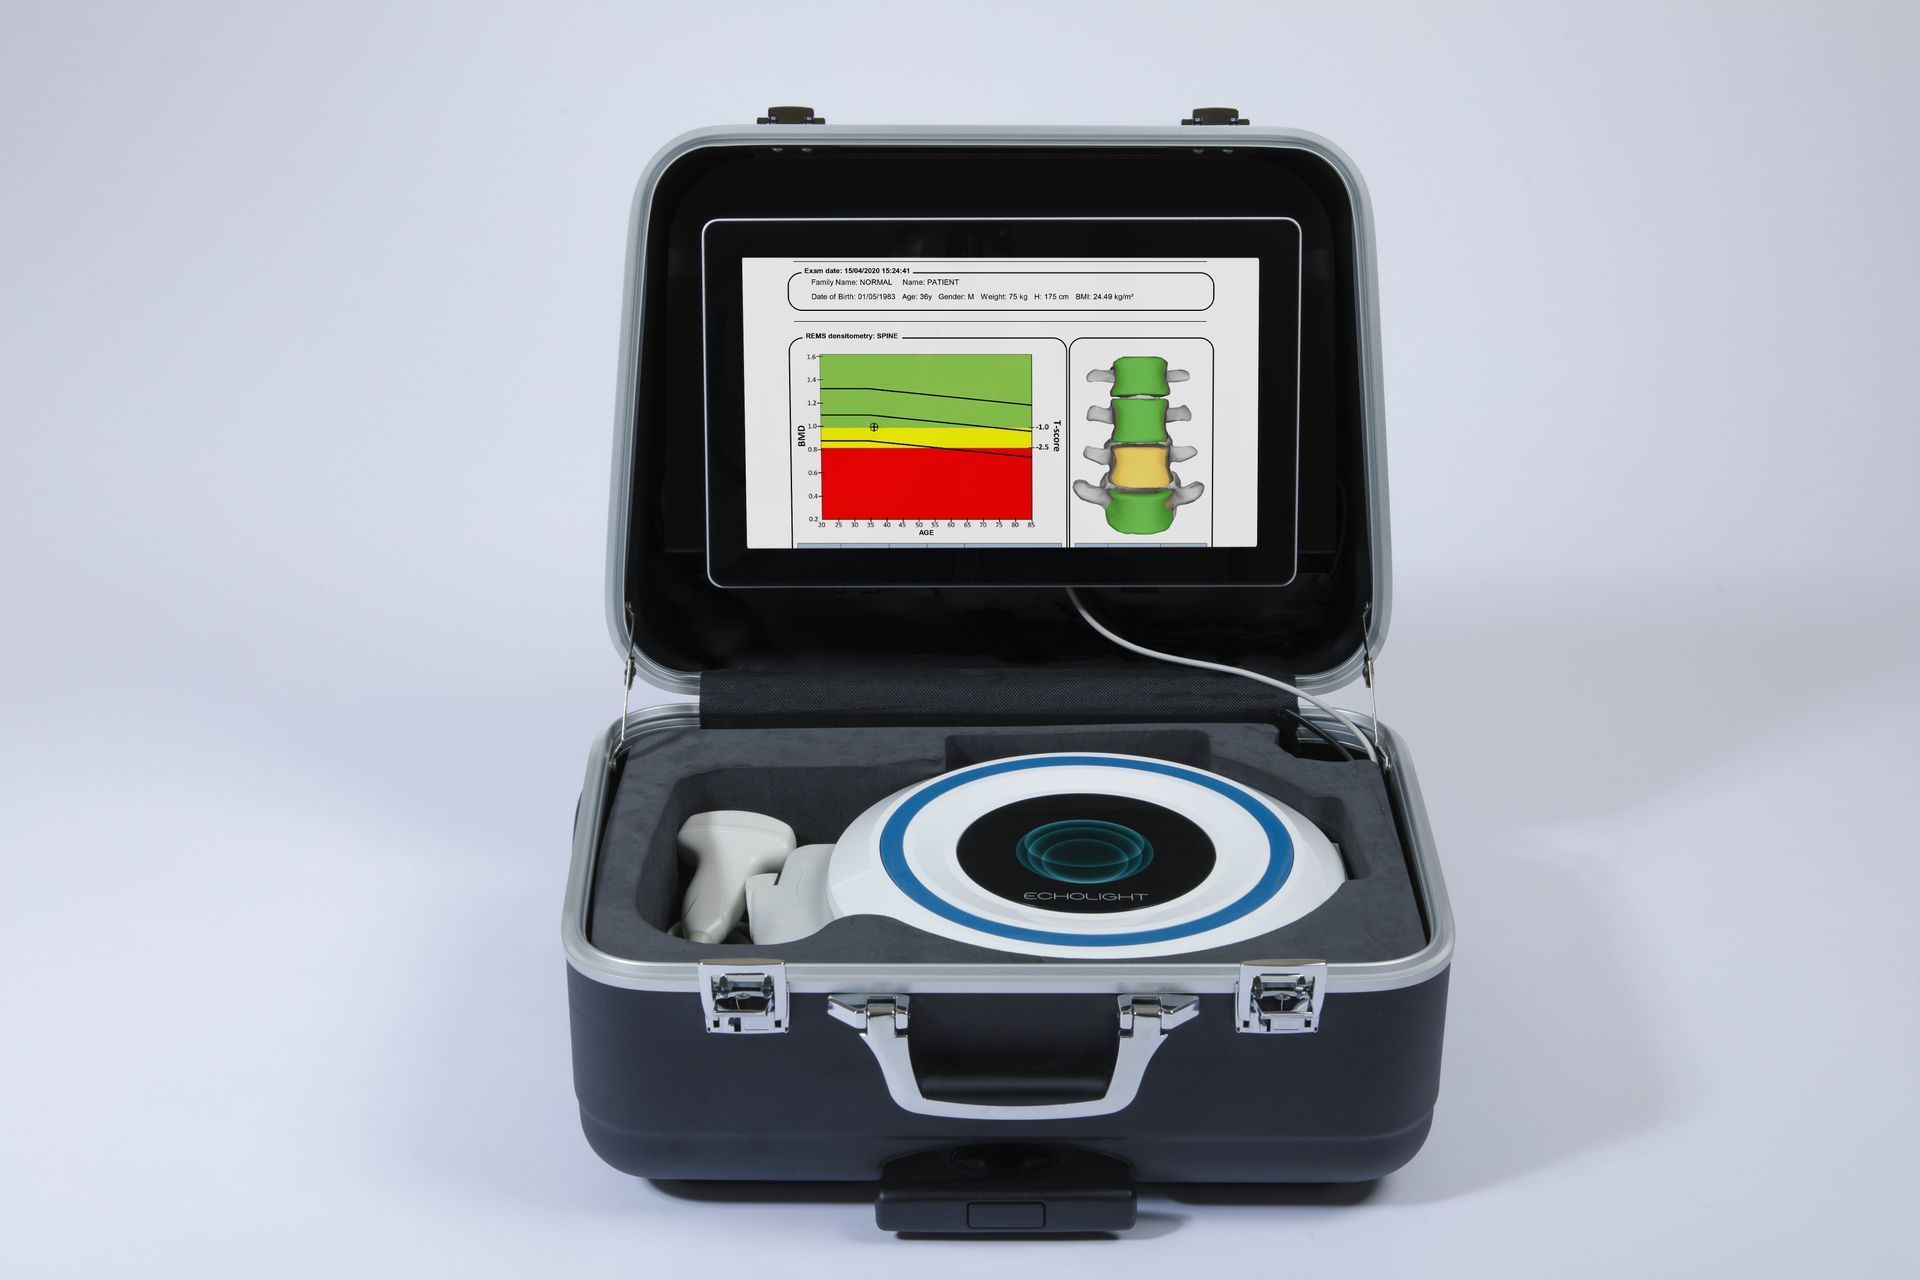
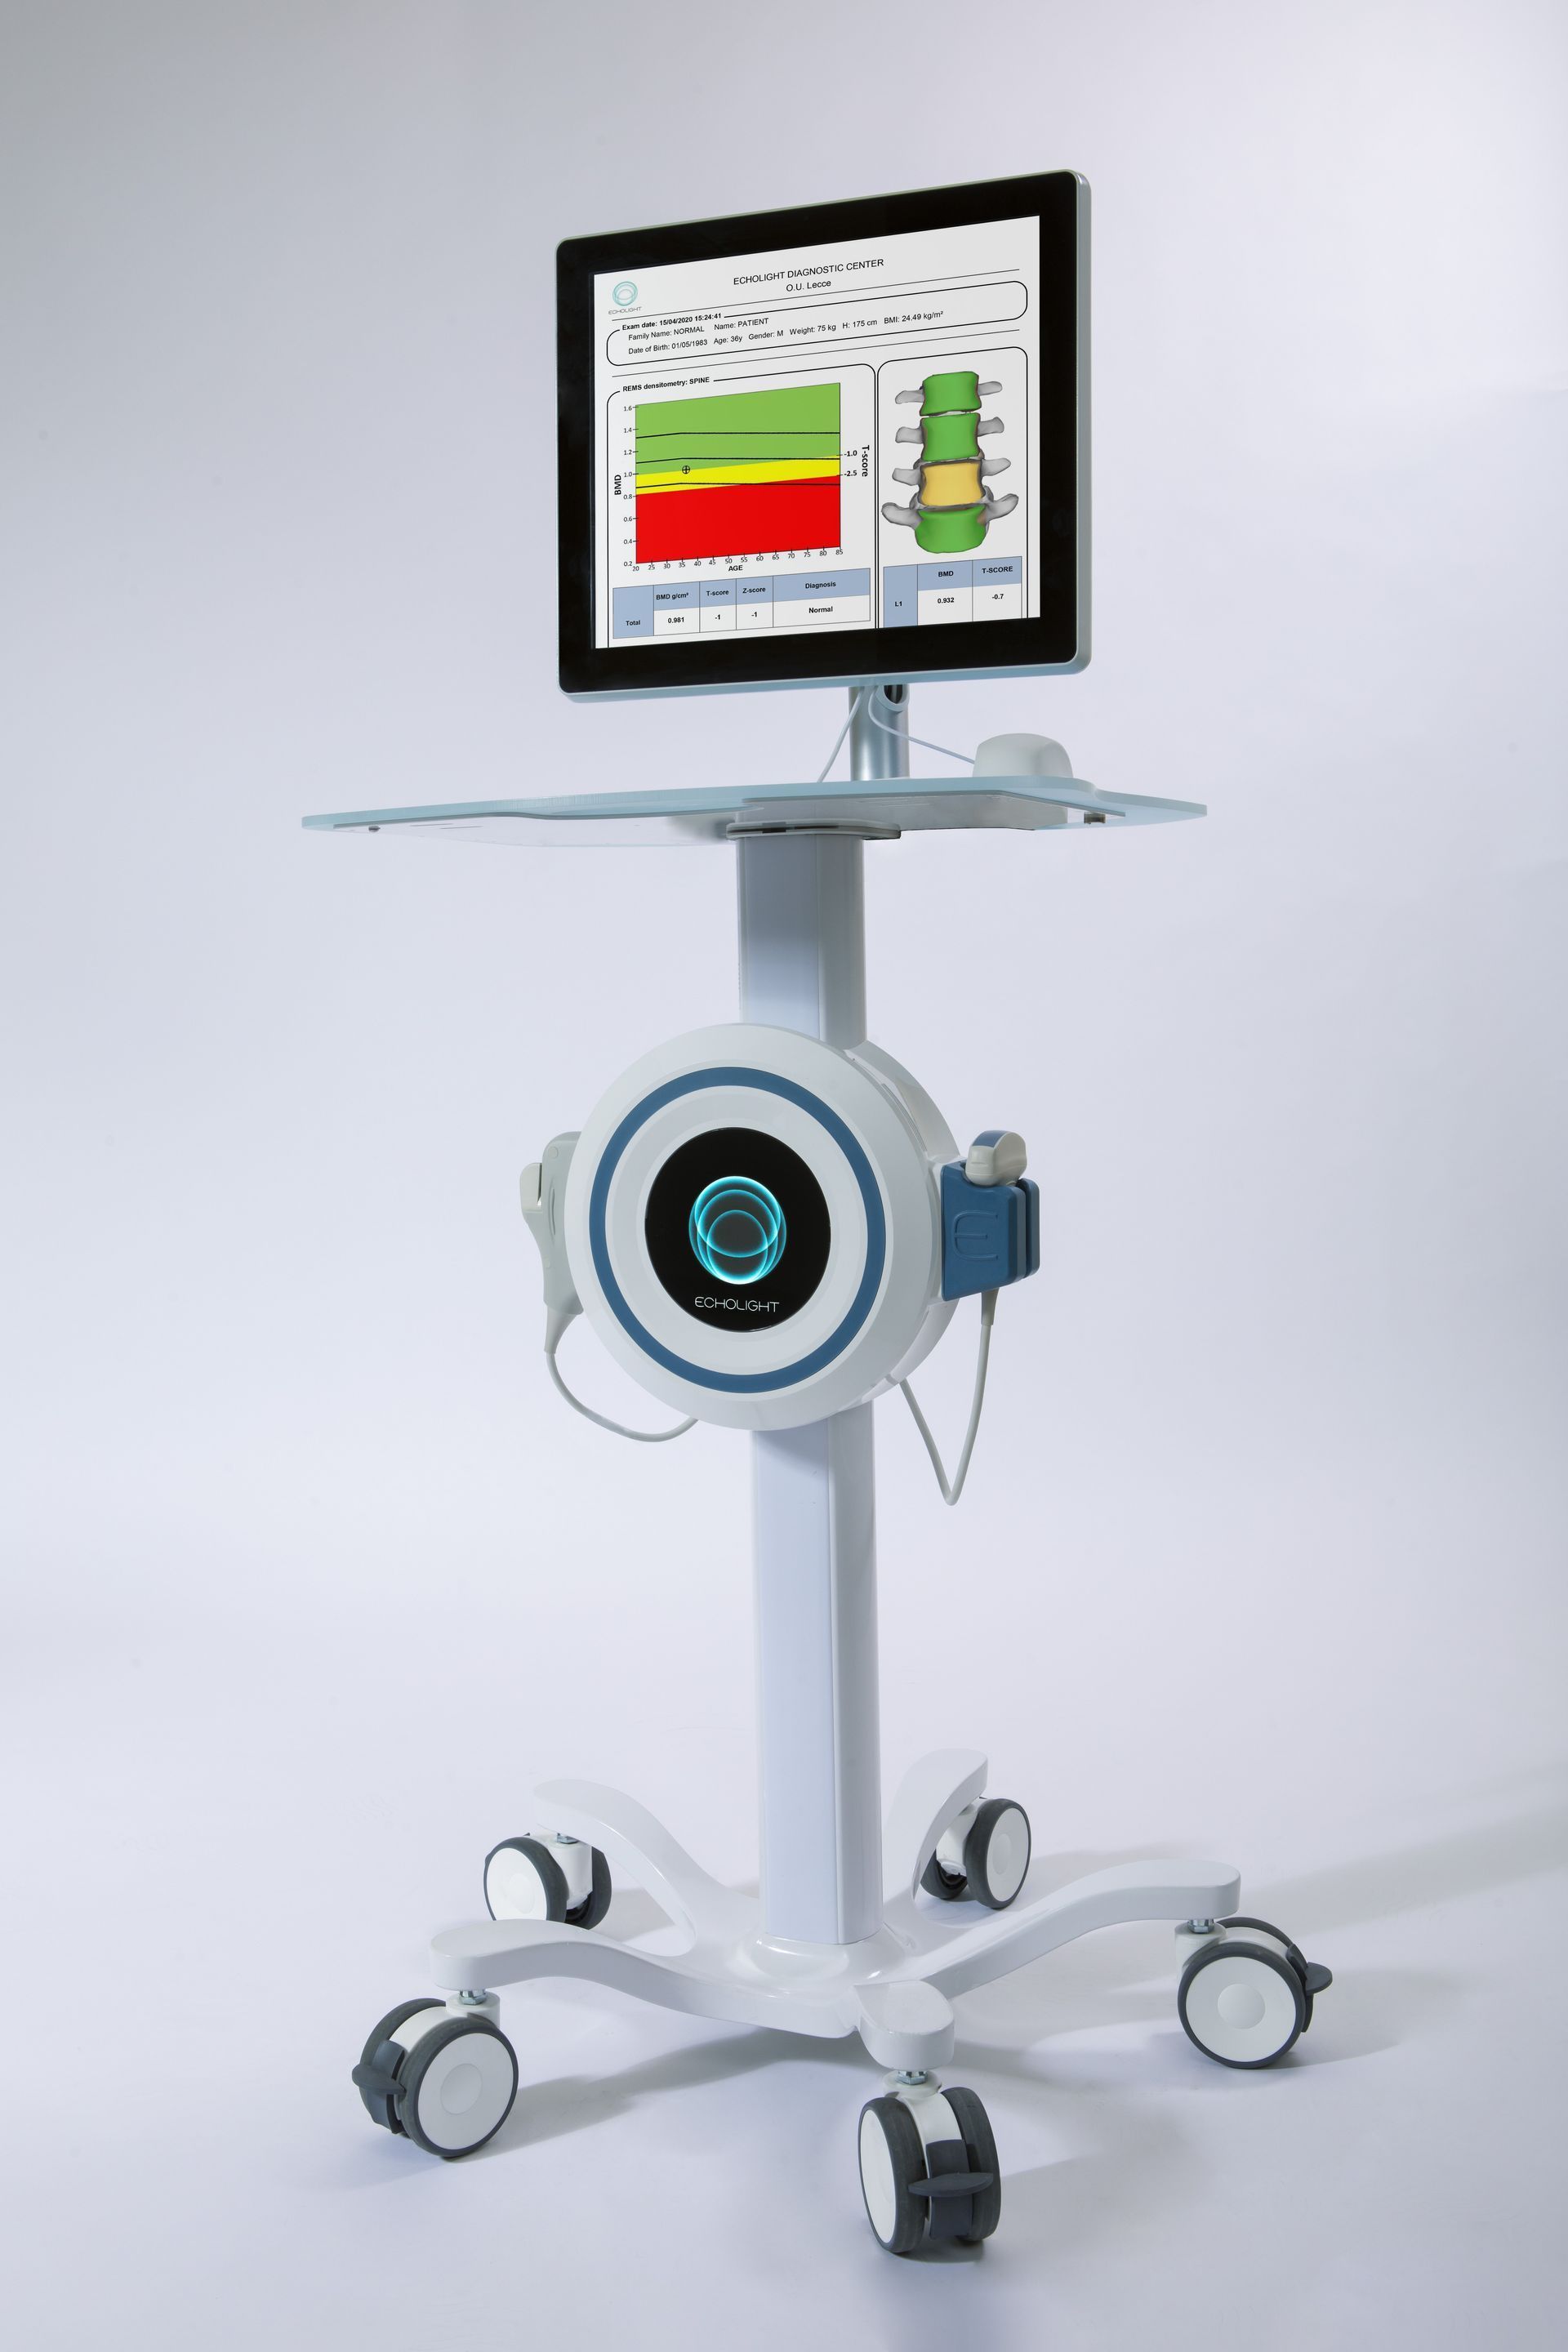
The generated reports following the completion of a REMS assessment include BMD, T-scores, Z-scores, the diagnosis, Fragility Score (FS) and Body Composition Analysis. The REMS reports are standardized and therefore they are uniform between all REMS systems.
Can REMS replace DXA as an accurate/precise method to assess bone?
REMS made sonographic assessment of the lumbar spine and proximal femurs possible. Until the EchoS was introduced, those regions could only be measured by DXA. DXA has been recognized as the standard method for BMD determination since 1987. Recent clinical studies have shown that REMS has the capacity to provide a reliable (accurate) and reproducible (precise) measurement of BMD as compared to DXA. In the cited studies, multiple authors converged on the conclusion that there is a high correlation between DXA-measured and REMS-measured BMD and T-score values, and that REMS had high accuracy, sensitivity, and specificity for the diagnosis of osteoporosis when compared to DXA. REMS is a new technology in the United States and Canada. The Food and Drug Administration (FDA) and Health Canada have fully and approved REMS technology for to measure BMD and determine fracture risk. REMS already has wide clinical acceptance within the European Union. Recently, REMS technology has been recognized as “the first ultrasound-based method to diagnose osteoporosis and assess the risk of fragility fractures” by the Italian National Institute of Health and it has been officially included in the Italian Ministerial Guidelines for the “diagnosis, risk stratification and continuity of care following fragility fractures.”
What is the reliability of the measurements made during a REMS examination?
Multicenter clinical studies demonstrated a good level of precision (intra-operator repeatability) and repeatability (inter-operator repeatability). For each reference site 30 patients were scanned, undergoing two consecutive investigations with repositioning in-between, in line with the ISCD guidelines. Precision was assessed on data acquired on two investigations performed by an experienced operator, whereas repeatability was assessed on data acquired on two investigations performed by two different operators, an experienced one and another who had previously received a short training. Factors associated to high precision and repeatability are explained by to:
- Automation of the data analysis.
- No need for any specific patient positioning due to the use of a hand-held transducer.
- No equipment component that undergoes a time dependent degradation process.
PARAMETER REMS DXA DXA
- Smallest Detectable Difference 0.006 - 0.009 g/cm2 0.0400-0.047 g/cm2
- 0.030 g/cm2
- Least Significant Change (LSC) 0.38 – 1.05% 4.93 – 5.60% 4.07%
- Intra-Operator Repeatability 0.32 – 0.36% 1.78 – 2.02% 1.47%
- Inter-Operator Repeatability 0.48 – 0.54% N.D. N.D.
As shown in the European studies, REMS accuracy and precision was validated with respect to DXA, demonstrating its effective clinical use for the diagnosis of osteoporosis according to the WHO criteria. Therefore, as documented in the above charts, REMS can be used to monitor BMD and provide information that is accurate, precise, and reproducible in a patient over time without many of the concerns that plague DXA.
Limitations & Errors in the Use of DXA for Monitoring Bone Health & Determining Fracture Risk.
There are well-known and documented concerns when DXA is used to determine fracture risk. A significant limitation of DXA densitometry is that it only determines BMD. The intrinsic errors that are associated with x-ray densitometry are also of concern. Concerns ranging from the detrimental effects of cumulative of x-ray exposure especially at younger ages to the stringent testing and positioning protocol that DXA requires to ensure a reasonable level of reliability. Several additional issues and concerns are listed:
- Small bone bias is a known intrinsic limitation of utilizing a method of bone assessment where information obtained during the quantitative measurement of a three-dimensional targeted ROI is analyzed and reported in a two-dimensional format.
- Calibration requirements due to recognized cathode ray tube degradation over time.
- Artifact susceptibility due to the limitations of utilizing x-ray beam attenuation differential as the method of bone assessment.
- Strict positioning requirements for attenuation coefficients to be valid and applicable.
- Non-standardized lumbar spine databases between DXA manufacturers.
- Long-term health concerns due to exposure to repeated doses ionizing radiation over time for serial bone health monitoring.
- Both short-term and long-term health concerns for younger individuals during child-bearing years due to the repeated exposure to ionizing radiation.
- No capability for quantitative quality assessment without the appropriate Trabecular Bone Score (TBS) software. TBS has been shown to have a predictive value for fracture risk, but this feature is not yet widely available or routinely utilized.
Based on the ISCD Official Position the minimum acceptable precision of a DXA technologist is:
Region Of Interest Precision Error Least Significant Change
- Lumbar Spine 1.9 % 5.3 %
- Total Hip 1.8 % 5.0 %
- Femoral Neck 2.5 % 6.9 %
Why should we reconsider how fracture risk is determined – Bone Strength vs BMD?
Historically, Bone Mineral Density (BMD) has been the default value for determining fracture risk. However, it is now recognized that, although low BMD values are associated with an increased risk of fracturing, BMD is not the absolute determinant of fracture risk. There are individuals with low BMD values that never fracture and conversely, a large percentage of individuals who sustain fragility fractures have BMD values that are above the osteoporotic range. There have been recent improvements in the understanding of bone structure and new capabilities are now available for quantitative measurements using novel technologies. Therefore, it is now universally accepted that multiple properties of bone need to be assessed to be able to correctly predict fracture risk. “Bone quality” is a term that is now ascribed to important structural properties of bone.
The “strength “of a material is a standard engineering term that describes the capacity of the material to withstand applied forces and not fail. Therefore, it is appropriate to use the term strength to describe the ability of a bone not to fracture due to an applied force. The strength of a material is a function of multiple physical properties of the material which include its microstructural properties. BMD and bone quality are two of the microstructural properties of bone. Infrared spectral analysis of bone biopsy specimens, determined that factors such as bone crystal size and collagen maturity, have a predictive value for fracture risk. It is now recognized that bone quality is a composite description of multiple microstructural properties of the bone which include the bone-mineral composition, the microarchitecture and the presence and the amount of micro fracturing present in addition to the amount and the integrity of the collagen components and the correct collagen-crosslinking. These properties are all integral components of the bone mineral crystal. BMD and bone quality are now considered to be the critical properties that determine bone strength. Consensus is growing that the term “bone strength” should replace “bone quality” when assessing bone structure.
In summary, the ability of a bone to withstand applied forces and not fracture should now be referred to as the bone strength. Bone strength is believed to be a composite property of the bone which consists of the density (BMD) and the bone quality. Recommendations are for both properties to be assessed to determine bone health and fracture risk.
The Fragility Score (FS) – REMS Unique Capability of Determining Bone Strength/Fracture Risk
The single most compelling aspect of REMS technology is the ability to assess bone quality and provide a predictive tool for fracture risk utilizing the FS. It is well documented in the literature that specific backscatter RF signals contain information on the microarchitecture of the target bone. A recently completed cross-sectional clinical study examined the ability of the REMS derived FS to distinguish between fractured and non-fractured patients. The FS has shown the ability to discriminate between patients who experienced an osteoporotic fracture from those who did not (sensitivity = 76%; specificity = 68%) as compared to DXA BMD (73% and 66% respectively). A recent work resumed a 5-year longitudinal study validating the use of the REMS-derived FS as a predictive tool for fracture risk.
How much does a REMS unit cost?
The Echolight REMS unit is afforable, and cost depends on if you would like to purchase your own unit, partner with a local REMS technician to offer REMS scanning at your facility, or share ownership with nearby like-minded medical providers. We'll work with you to determine the best path for your particular practice and help make all the necessary connections to bringing REMS technology to your practice.
View sample REMS reports from actual patients
Still have a question about REMS?
Want to add Echolight REMS scans to your practice?

Get the BoneForte Patient Portal for Your Medical Practice
If you're a medical professional interested in leveraging data to provide your patients online self-scheduling and appointment management, HIPAA-compliant medical record access, and secure bill payment, we'd love to chat with you about bringing the BoneForte Patient Portal to your practice.